Innerslice
Turns a scan you cannot read into one you can.
The problem
You are handed a scan of your own body and have no way to read it.
An MRI comes back as a stack of gray slices that takes years of training to interpret. For the person inside those images, that leaves two options: guess, or take someone else's word for it. Neither tells you how big the tear is, where it sits, or what it touches. The tools that can answer those questions are built for radiologists and stay inside the hospital. Nothing in the chain is built for the patient.
What it makes possible
- 01
The scan as an object you can turn
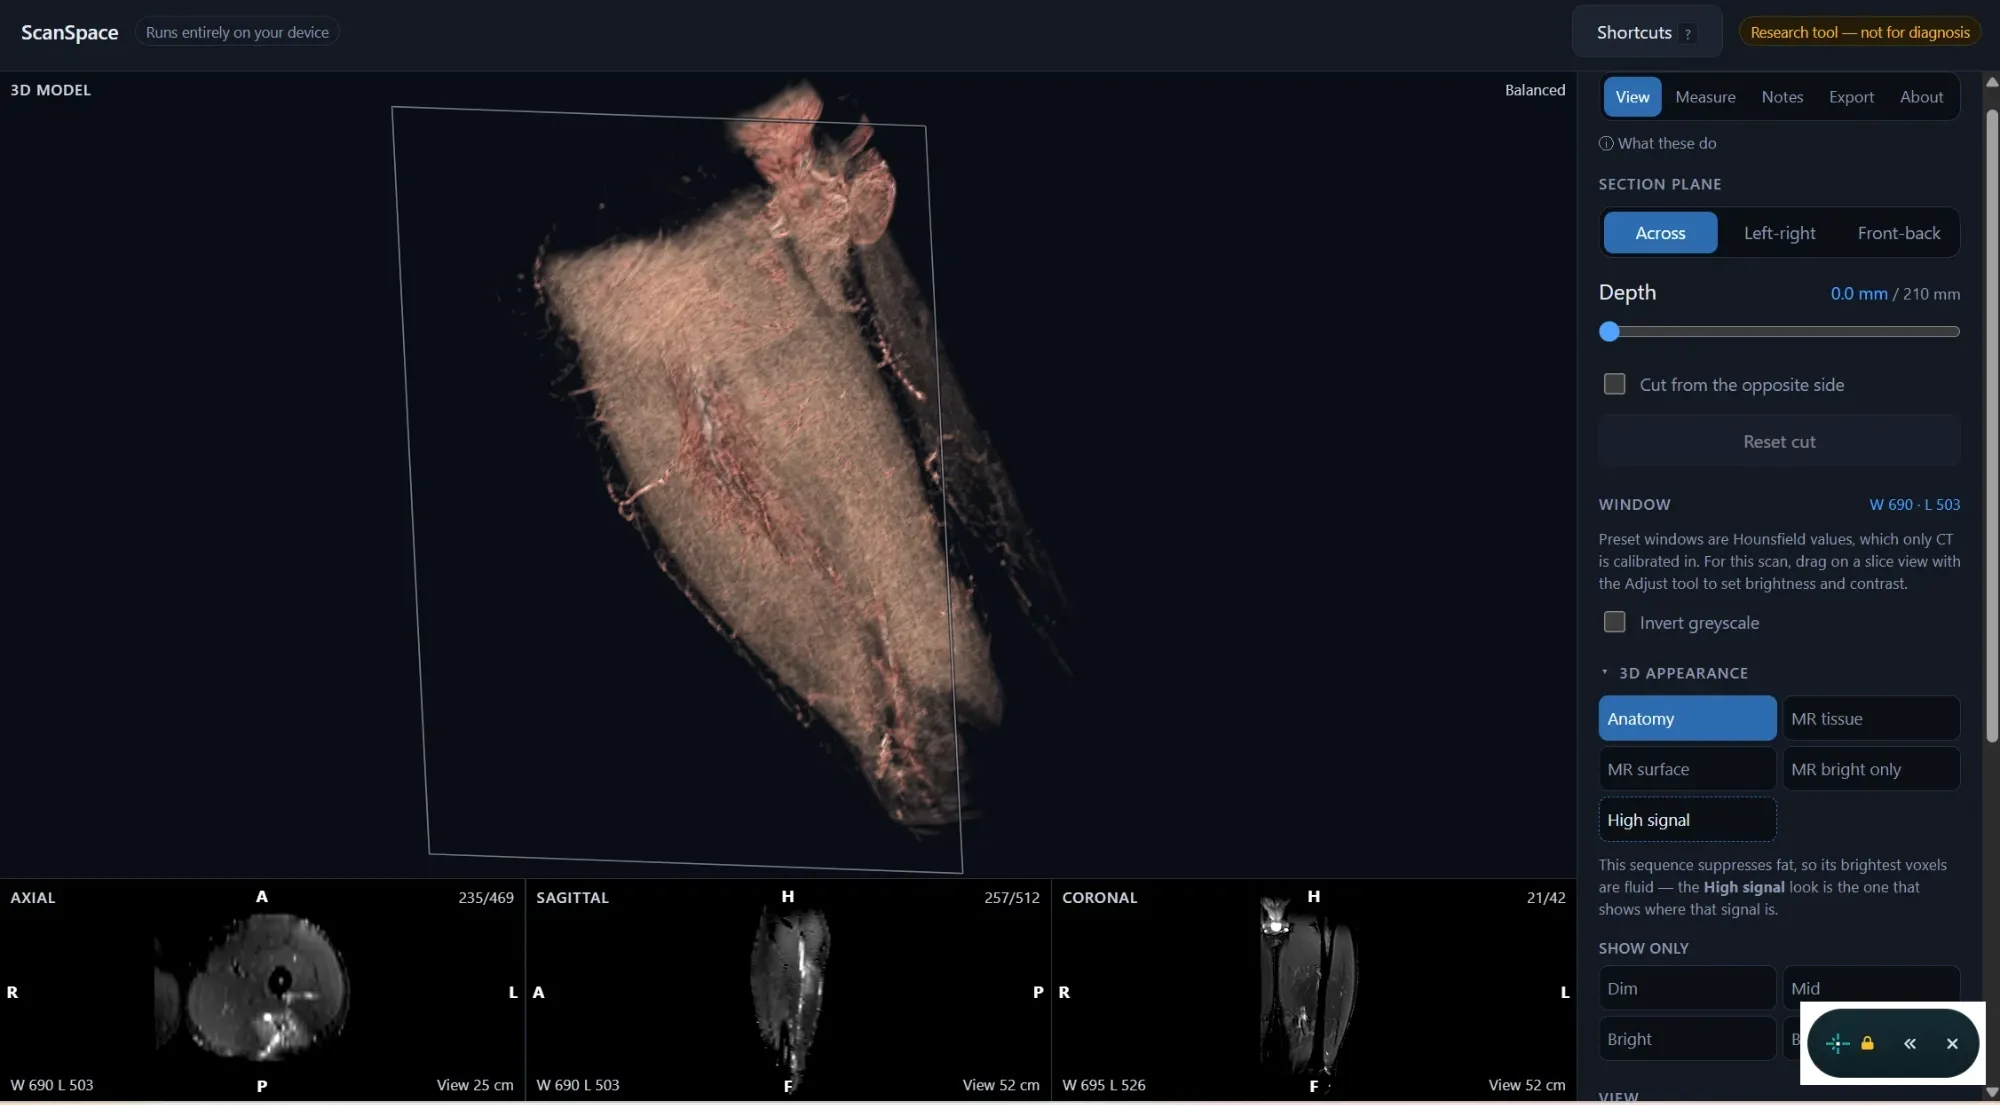
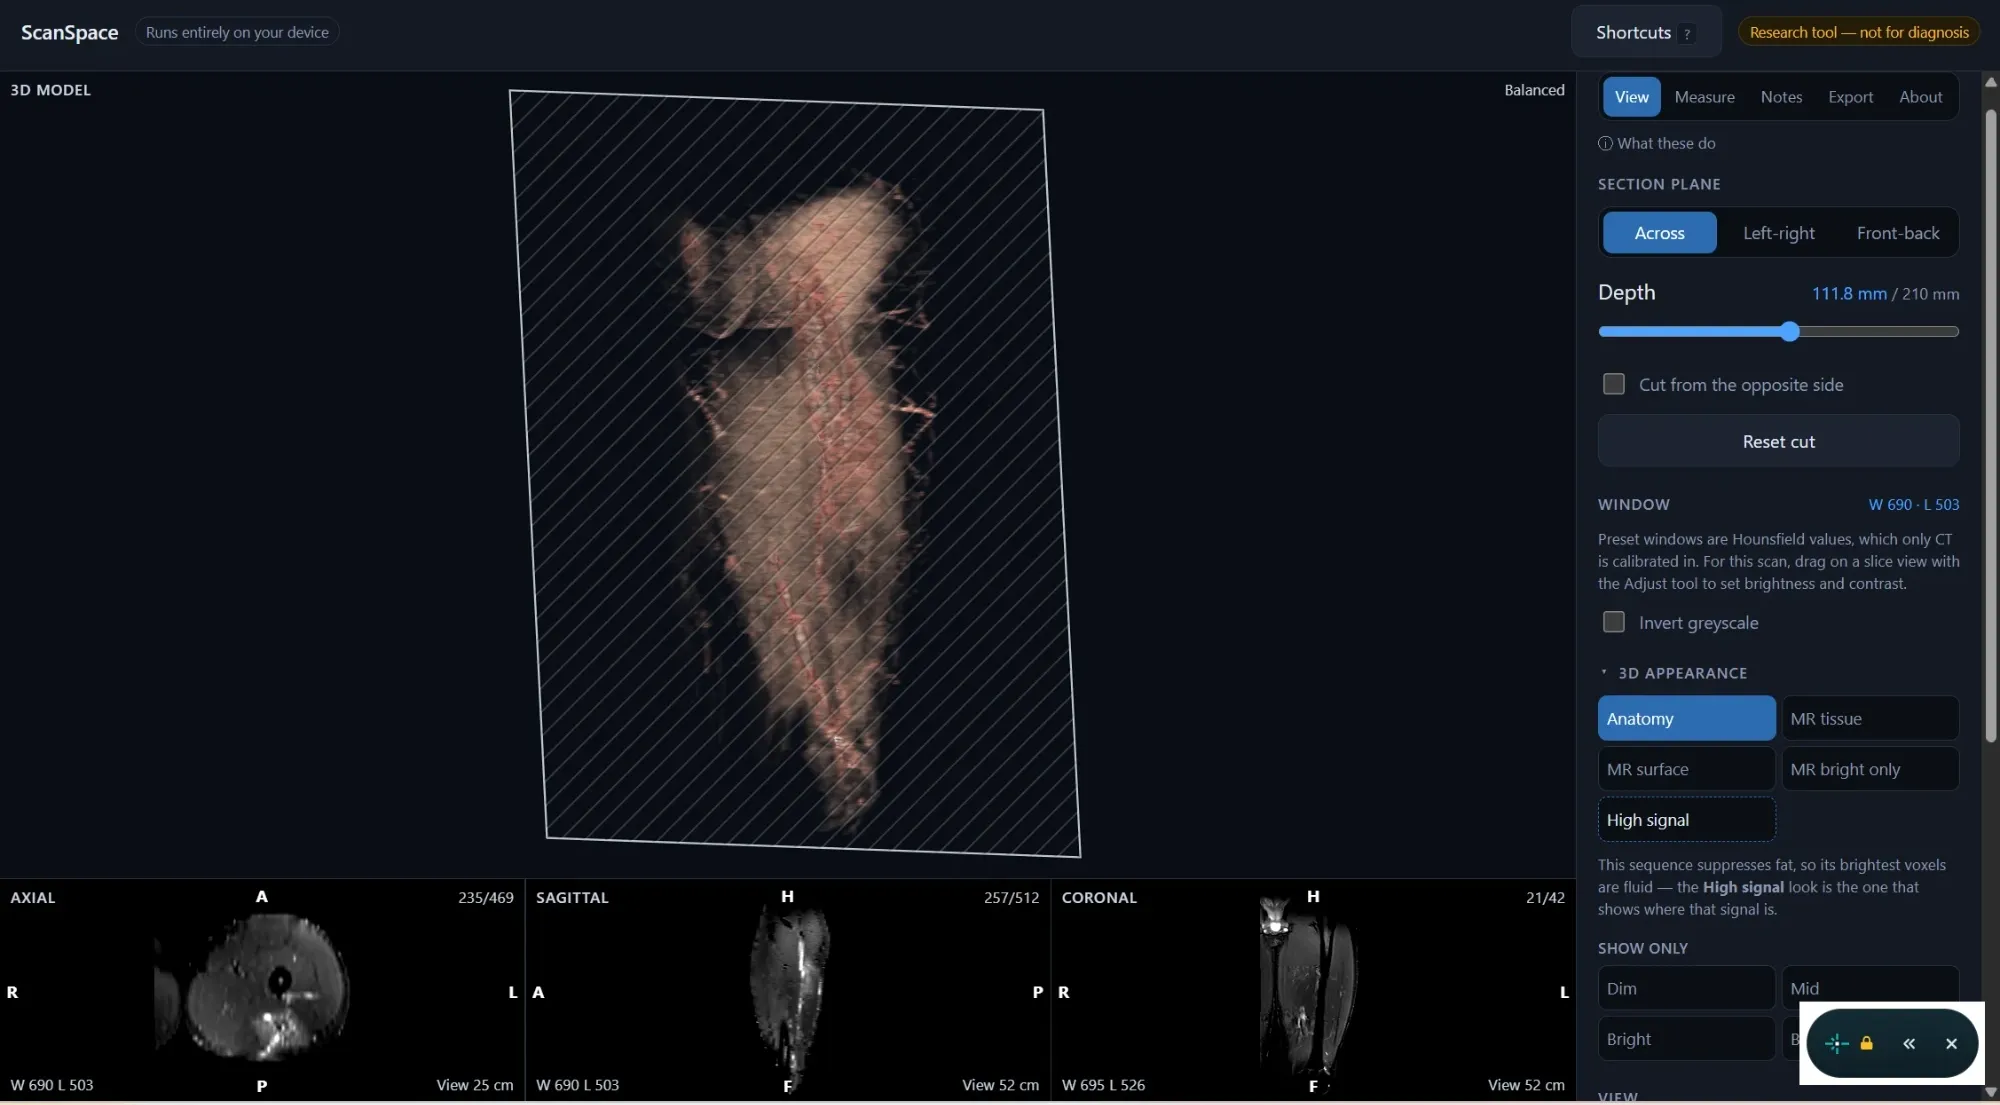
It reads a raw DICOM folder and keeps only the series worth rendering (270 of 559 files on my own study). What comes back is a model built from the scan's own dimensions, rotated and viewed from any side, with a section plane to cut through it at any depth and the axial, sagittal and coronal slices tracking alongside.
- 02
A real measurement of the injury
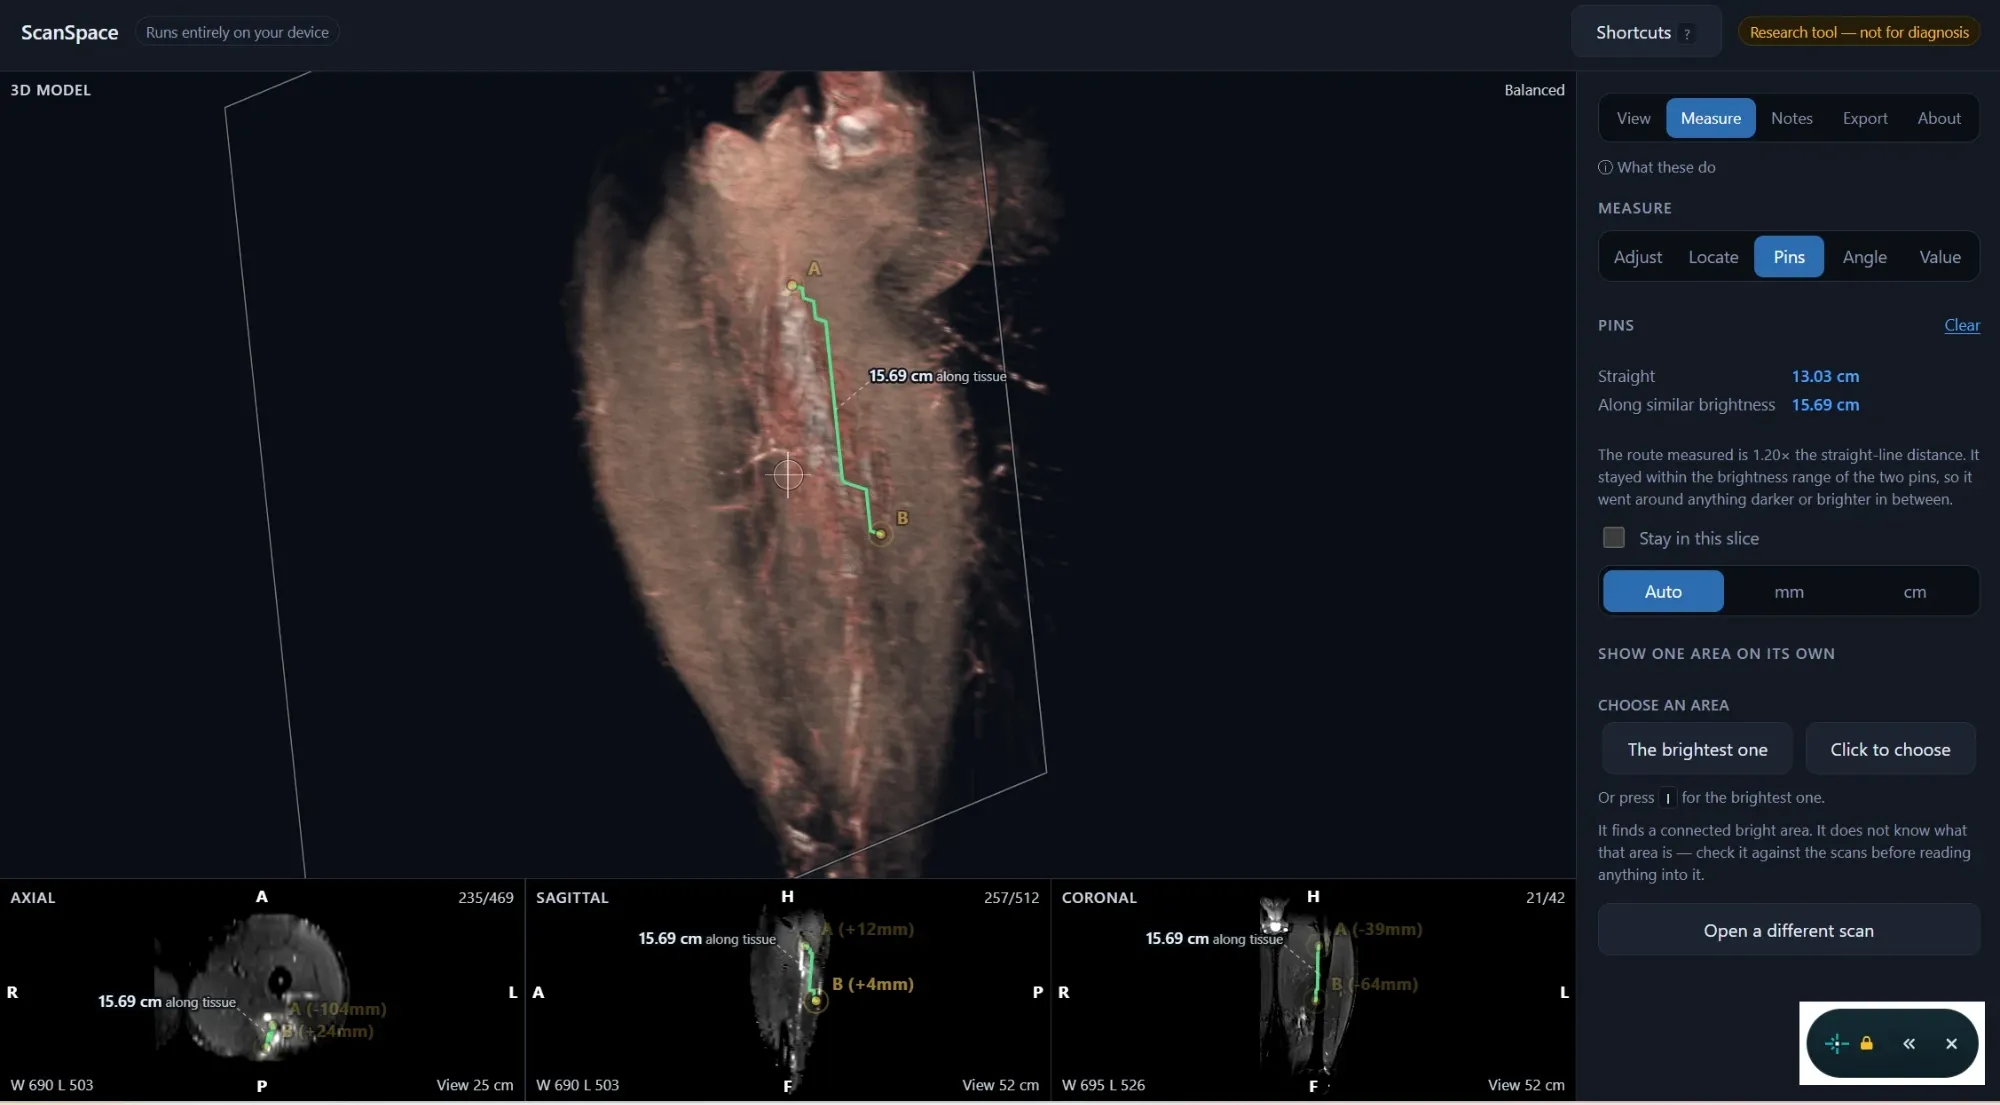
Two pins measure the actual route through the tissue between them rather than the straight line, so the number follows the structure it belongs to instead of cutting across whatever is in the way. On a hamstring tear that came out a fifth longer than the straight-line figure.
- 03
Nothing leaves your machine
The scan is read and rendered in the browser, so nothing is uploaded and no account stands between a person and their own images. There is no backend at all, which means nothing to pay for and no store of medical images to breach.
- 04
The doctor marks it up, the patient receives it
Pins and notes record where the damage is and how severe, then reach the patient as a simpler view of the same model, so the explanation arrives attached to the thing being explained.
- 05
What to stay off while it heals
Given the injury, it lays out which movements are likely to load that muscle and which are safer while it recovers. The guidance is general rather than tailored to the person for now, and it is advice on what to avoid, not a diagnosis.
- 1.20×Measured path vs straight line
- ~10 sFolder to a model you can turn
- 0Images uploaded anywhere
In use
Notes
Where it came from
I tore my hamstring and could not read my own MRI. I wanted to see what had happened, so I built something that would show me. Knowing what was actually there turned out to matter more than I expected. It is a strange kind of helplessness to be handed an image of your own body and have no way in.
It says what it does not know
The interface is labeled a research tool rather than a diagnostic one, and the region finder says outright that it has located a connected bright area without knowing what that area is. A tool aimed at people reading their own scans has to be clear about where its answers stop.
The stress guidance is the sharpest case. It is general advice about what loads a muscle, not a reading of this person’s body, and whether a patient should see it directly or only through their doctor is a question I have not settled.
Where it stands
A prototype with a live build, proven end to end on my own MRI. The next step is more scans: one case shows the idea works, and confirming it holds across different studies, body parts and machines needs data I do not have yet.
Where it goes
Two directions. The first is reach: a doctor sending you to your own annotated model through something like MyChart, so it is there whenever the questions come up, which is rarely while you are still in the office.
The second is movement, building on the stress guidance that already exists. Today that guidance is general: what tends to load a given muscle. The direction is to make it personal, taking someone’s own model through a motion cycle to find where the strain actually peaks and at which point in a stride. Knowing the shape of an injury tells you what happened. Knowing where the load peaks tells you what to stay off.